


There is a risk that Millennium Development Goals aimed at improving child and maternal mortality and expanding access to sanitation will be missed, the United Nations has warned.


Hundreds of pregnant women and girls are dying needlessly in South Africa. In part, this is because they fear their HIV status may be revealed as they access antenatal care services, according to a major report published by Amnesty International today.
Struggle for Maternal Health: Barriers to Antenatal Care in South Africa, details how fears over patient confidentiality and HIV testing, a lack of information and transport problems are contributing to hundreds of maternal deaths every year by acting as barriers to early antenatal care.
“It is unacceptable that pregnant women and girls are continuing to die in South Africa because they fear their HIV status will be revealed, and because of a lack of transport and basic health and sexuality education. This cannot continue,” said Salil Shetty, Amnesty International’s Secretary General.
“The South African government must ensure all departments work together to urgently address all the barriers that place the health of pregnant women and girls at risk.”
South Africa has an unacceptably high rate of maternal mortality. There were 1,560 recorded maternal deaths in 2011 and 1,426 in 2012. More than a third of these deaths were linked to HIV. Experts suggest that 60% of all the deaths were avoidable.
Antenatal care is free in South Africa’s public health system. However, Amnesty International’s research found that many women and girls do not attend clinics until the later stages of their pregnancy because they are given to believe that the HIV test is compulsory. They fear testing and the stigma of being known to be living with HIV. Nearly a quarter of avoidable deaths have been linked to late or no access to antenatal care.
Worryingly, these fears are not without foundation. Amnesty International’s report, based on field research conducted in Mpumalanga and KwaZulu-Natal provinces, contains testimonies from women and girls who say that health care workers inappropriately discuss HIV test results with others.
“The nurses are talking about people and their status”, a woman from KwaZulu-Natal explained.
Amnesty International also found that several clinics it visited use processes for pregnant women and girls living with HIV that disclose their status, including separate queues for antiretroviral medication, different coloured antenatal files and different days for appointments.
“[I]f I go for antiretroviral, my line is that side. All the people in this line they know these people are HIV. That’s why people are afraid to come to the clinic,” one woman in Mpumalanga told Amnesty International.
“During antenatal care, if women come out of the counsellor’s room with two files, then everyone knows they are HIV positive,” said another woman.
Women and girls said they feared discriminatory treatment even from partners and family members as a result of testing positive for HIV and that HIV-related stigma remained a problem in many communities.
“While HIV testing is an important public health intervention it must be done in a manner that respects the rights of women and girls and does not expose them to additional harm. It is deeply worrying that the privacy of pregnant woman and girls is not respected in health facilities. The South African government must take urgent steps to correct this,” said Salil Shetty.
“It is vital that health care workers in South Africa receive additional training on providing quality care that is both free of judgement and stigma and that women and girls accessing sexual and reproductive health services are able to trust that their confidentiality will be respected.”
Amnesty International’s report also identifies that a lack of information and knowledge about sexual and reproductive health and rights increases risks of unplanned pregnancies and HIV transmission, especially among adolescents. Likewise women and girls are often unaware of the importance of early antenatal checks.
The report also documents the lack of progress made in KwaZulu-Natal and Mpumalanga to ensure that women and girls can physically access health services. Problems persist relating to shortages of public transport and poor road infrastructure. The roads in some areas visited by Amnesty International are of such poor quality that they become impassable when it rains. Even when it is dry, ambulances will not go beyond a certain point on some roads. Amnesty International had documented the same problems in both provinces in a 2008 report.
“The South African government must build better road networks in these rural provinces to guarantee access to healthcare facilities. The government must also ensure that ambulances are always available to transport those who are in need,” said Salil Shetty.
This report builds on Amnesty International’s 2008 report, ‘I am at the lowest end of all’: Rural women living with HIV face human rights abuses in South Africa, in which the organisation documented gender, economic and social inequalities as barriers to health care for women living with HIV.
9 October 2014
By Amnesty International
Source: http://www.amnesty.org/en/news/south-africa-pregnant-women-and-girls-continue-die-unnecessarily-2014-10-09
 The sexual and reproductive health rights of young marginalized populations are often neglected and their collective voice in this critical area not always heard. To try to redress this imbalance young people from marginalized communities and key populations in Bangladesh, Ethiopia, Puerto Rico and Uganda met in New York this week to discuss how to put these rights issues firmly on the post-2015 development agenda, leaving no one behind.
Taking place on 25 September, the General Assembly side event which took the form of a panel discussion, examined the vital role of community engagement, advocacy and service delivery in protecting the rights and meeting the needs of young key populations. These include men who have sex with men, sex workers and young people living with HIV.
Young speakers, who were peer educators, directors of national and regional NGOs, actors and community leaders, argued that universal access to HIV services and health coverage could not be achieved without prioritizing the needs of the most marginalized. They also noted the contribution of comprehensive sexuality education to improving young people’s health and the role that communities can play in both promoting rights and challenging stigma and discrimination.
The event was hosted by the Government of Brazil and organized by the International HIV/AIDS Alliance, GESTOS, the Global Youth Coalition on AIDS, ATHENA, ICASO, International Civil Society Support, STOP AIDS NOW!, Stop AIDS Alliance, the HIV Young Leaders Fund, the African Services Committee, and the Global Forum on MSM and HIV, in collaboration with UNAIDS.
Quotes
"Setting goals is only part of the story. Where we should look for change is the way that we will implement the goals. We need to change the way we are doing business and craft the space for civil society in the new post-2015 agenda."
Luiz Loures, UNAIDS Deputy Executive Director
“We are talking about development here and sexual and reproductive rights are development."
Pablo Aguilera, HIV Young Leaders Fund
By UNAIDS
26 September 2014
Source: http://www.unaids.org/en/resources/presscentre/featurestories/2014/september/20140925csyoungpops/
In 2000, the creators of the Millennium Development Goals (MDGs) completely overlooked sexual and reproductive health and rights (SRHR), a mistake that, if repeated, would cripple the dreams of millions of young girls and women for years and generations to come.
Access to SRHR enables individuals to choose whether, when, and with whom to engage in sexual activity; to choose whether and when to have children; and to access the information and means to do so. To some, these rights may be considered an everyday reality. However, that is not the case for millions of young people in the world – particularly girls and women.
On Tuesday night, I had the fantastic opportunity to listen to some of the foremost global leaders speak on behalf of ensuring access to sexual and reproductive health and rights in the post-2015 agenda. The benefits of ensuring SRHR are society wide and inevitably translate into improved education, economic growth, health, gender equality, and even environment.

“At my high school, you would be expelled if found with a condom.” – Samuel Kissi, former President, Curious Minds Ghana
When girls are healthy and their rights are fulfilled, they have the opportunity to attend school, learn life skills, and grow into empowered young women. Wherever girls’ SRHR are ignored, major educational barriers follow. Child marriage and early pregnancy are major contributors to school dropout rates. In South Asia and Sub-Saharan Africa, girls are married before age 18 at an alarming 50 percent and 40 percent respectively. And in Sub-Saharan Africa, where 90 percent of adolescent pregnancies occur in marriage, it is safe to assume that not all those sexual acts were consensual and not all those pregnancies were planned.
“Initially I used to oppose family planning, but now I fully support. I support it because my wife has more time to work and earn money.” – The Honorable Dr. Tedros Adhanom Ghebreyesus, Minster of Foreign Affairs for the Federal Democratic Republic of Ethiopia, sharing the story of an Ethiopian man’s changed opinion regarding the importance of SRHR
Protecting SRHR not only saves lives and empowers people, but it also leads to significant economic gains for individuals and for the community as a whole. As previously stated, ensuring SRHR helps to decrease school dropout rates and, as a result, leads to a more productive and healthy workforce as each additional year of schooling for girls increases their employment opportunities and future earnings by nearly 10 percent.
“We cannot eliminate new HIV infections without providing SRHR services to women so they can make informed decisions to protect themselves and their children in the future. Yes, we will end the AIDS epidemic, but first we need to respect the dignity and the equality of women and young girls.” – Dr. Luiz Loures, Deputy Executive Director, UNAIDS
Access to SRHR guarantees quality family planning services, counseling and health information. These services are critical, particularly because women are often victims of gender-based violence and sexual assault and thereby face greater risks for sexually transmitted diseases like HIV/AIDS. Failing to secure and uphold SRHR dooms women and girls with an increased risk of unsafe, non-consensual sex and maternal mortality.
“How can you control your life if you cannot control your fertility?” – Helen Clark, UNDP Administrator
When a woman can easily plan her family, she is more equipped to participate in the economy alongside her male colleagues. When the sexual rights of a woman or girl are fulfilled, she will experience decreased rates of sexual violence and enjoy a healthy relationship with a respectful partner. When a woman or girl does not fall victim to child marriage and early pregnancy, she can stay in school and achieve anything she puts her mind to.
“The woman continues to bring life, to bring up the next generation, to stand before you and say, ‘I am ready to embrace my rights and to deliver a better planet to humanity.’” – Joy Phumaphi, former Minister of Health, Botswana; Chair, Global Leaders Council for Reproductive Health

A 2012 study found that community water and sanitation projects designed and run by women are more sustainable and effective than those that are not. Similarly, women produce 60 to 80 percent of food in developing countries and, with the economic and educational gains that coincide with secured SRHR, a woman is better equipped to effectively manage her land.
The post-2015 Sustainable Development Goals will not happen without SRHR being addressed. So far, the world has failed to recognize that SRHR are equally as fundamental to global development as finance and trade. We can no longer afford to view SRHR as a taboo or promiscuous topic. When 90% of first births in low-income countries are to girls under 18; when the leading cause of death among adolescent girls aged 15 to 19 is pregnancy and childbirth; when two-thirds of new HIV infections in sub-Saharan Africa are among adolescent girls; and when 200 million women want to use family planning methods but lack access, the young girls and women of the world do not have a promiscuity problem – they have a human rights problem.
By Elisabeth Epstein
25 September 2014
Source: http://girlsglobe.org/2014/09/25/we-cant-have-a-post-2015-agenda-without-srhr/
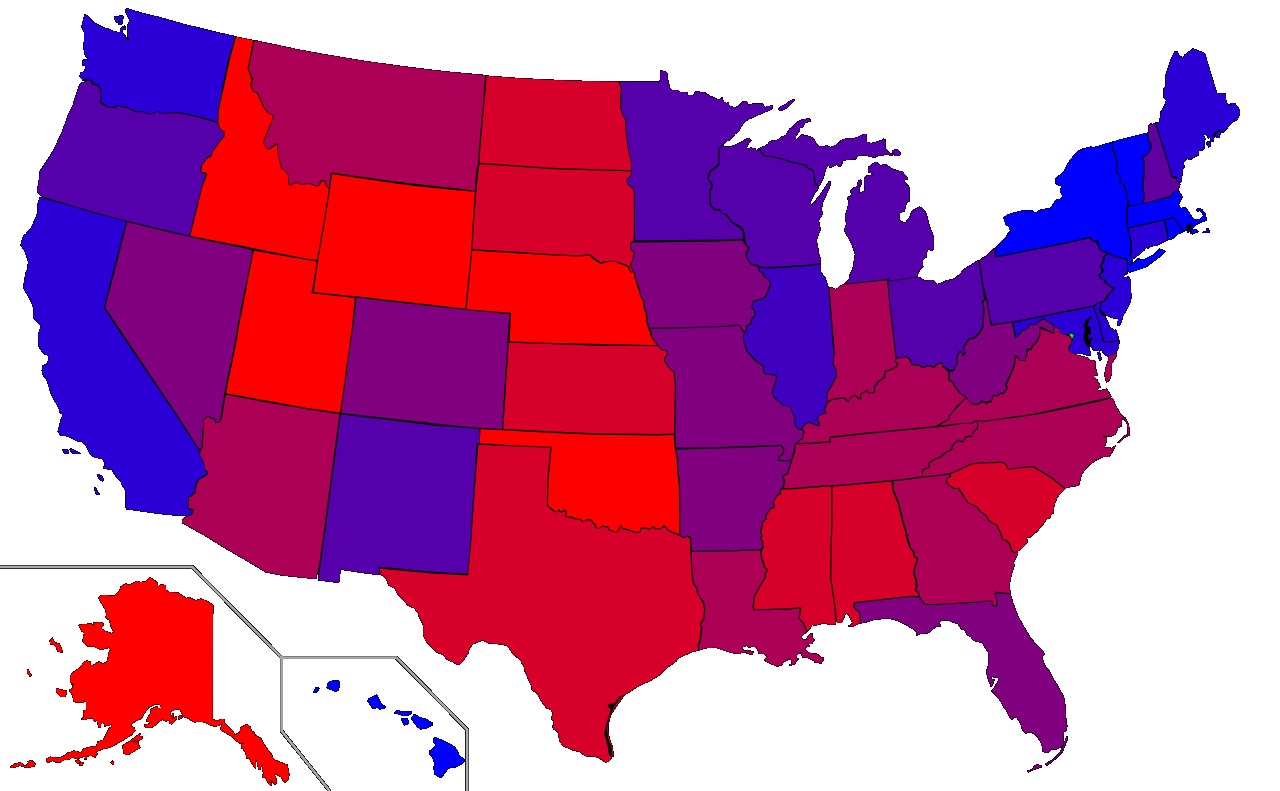
A new national survey reveals that the political divide among red-versus-blue states does not support the hypothesis that knowledge about abortion and health is shaped by the state in which one lives.
August 19, 2014
Research led by Danielle Bessett, a University of Cincinnati assistant professor of sociology, was presented at the 109th Meeting of the American Sociological Association in San Francisco.
Bessett says that regardless of political viewpoints, only 13 percent of the 569 people polled in the national survey demonstrated high knowledge of abortion, correctly answering four or five questions. Seven percent mistakenly thought that abortion until 12 weeks gestation was illegal (another 11 percent didn't know if it was illegal or not).
More than half the sample (53 percent) reported living in a blue (considered liberal) state; 26 percent reported living in a red (considered conservative) state and 20 percent reported living in a "purple" state – swing states such as Ohio, in which Democrats and Republicans have strong support.
Although initial results showed some support for the red-versus-blue state divide when it came to abortion health knowledge (but not legal knowledge), this difference between states disappeared when researchers took into account individual-level characteristics, including respondents' political beliefs, their beliefs about whether abortion should be permitted and whether or not they knew someone who had an abortion.
"Because the issue of abortion is an exemplar of polarization, it provides a useful way to test the red states v. blue states hypothesis," write the authors. Bessett says she and her co-researchers found that their "data does not support the red-versus-blue state hypothesis: geography does not dictate the world views of Americans. Some individuals in all settings do have accurate information about abortion, regardless of political context."
An online questionnaire was administered to 586 randomly selected men and women ages 18 to 44 via SurveyMonkey Audience. The findings focused on answers from 569 respondents (91.7 percent of the sample) who were born in the U.S. Participants responded to five survey items related to knowledge about abortion health and one exploring legal knowledge about abortion:
Survey Questions
· What percentage of women in the U.S. will have an abortion by age 45?
Correct answer: 33 percent
Percentage of respondents with correct answer: 41 percent
· Which has a greater health risk: An abortion in the first three months of pregnancy or giving birth?
Correct answer: giving birth
Percentage of respondents with correct answer: 31 percent
· A woman who has an abortion in the first three months of pregnancy is more likely to have breast cancer than if she were to continue the pregnancy.
Correct answer: disagree somewhat/disagree strongly
Percentage of respondents with correct answer: 37 percent
· A woman who has an abortion in the first three months of pregnancy is more at risk of a serious mental health problem than if she were to continue that pregnancy.
Correct answer: disagree somewhat/disagree strongly
Percentage of respondents with correct answer: 31 percent
· A woman having an abortion in the first three months of pregnancy is more likely to have difficulty getting pregnant in the future.
Correct answer: disagree somewhat/disagree strongly
Percentage of respondents with correct answer: 35 percent
· Abortion during the first three months of pregnancy is legal in the U.S.
Correct answer: true
Percentage of respondents with correct answer: 83 percent
Based on their findings, the researchers conclude that men and women making sexual and reproductive health decisions may not be well informed about the relative safety and consequences of their choices, highlighting a need for the provision of better, more comprehensive and evidence-based sexual and reproductive health education.
Survey Demographics
Fifty-three percent (313) of the respondents were male; 47 percent (273) female; 49 percent reported an age between 18-29 and 51 percent reported being between 30-44; the majority of the respondents (78 percent) identified as white; 11 percent Hispanic; four percent black and seven percent identified as "other" race or ethnicity.
Thirty-seven percent described themselves as very or somewhat liberal, 38 percent felt they were moderate and 25 percent identified as somewhat or very conservative.
Forty-one percent did not affiliate with any religion, 16 percent identified as Catholic and 35 percent identified as Protestant. Twelve percent reported they had a personal experience with abortion and 65 percent reported knowing someone who had an abortion. Eighty-seven percent believed that in most instances, abortion should not be restricted.
Additional authors on the paper are Caitlin Gerdts, an epidemiologist at University of California, San Francisco; Lisa Littman, an adjunct professor of preventative medicine at the Icahn School of Medicine at Mount Sinai Hospital; Megan Kavanaugh, Guttmacher Institute; and Alison Norris, MD, assistant professor, College of Public Health, The Ohio State University.
Source: University of Cincinnati
http://www.news-medical.net/news/20140819/New-study-highlights-the-need-for-evidence-based-sexual-and-reproductive-health-education.aspx
August 18 marks 500 days remaining before the Millennium Development Goals expire at the end of 2015. Some countries are on track to meet those goals and some are not, and central to the difference is their relative levels of investment in women and girls.
The MDGs emerged from an historic summit of world leaders to mark the new millennium nearly 15 years ago. Since then, countries that worked to boost girls’ education, women’s rights and comprehensive maternal, sexual and reproductive health care saw benefits not just for gender equality and longer lives for women and children but in other areas as well — against poverty and hunger, against diseases including HIV and AIDS, and toward a more sustainable environment. Investment in girls and women turned out to be the most cost-effective way to advance on all the goals.
Women Deliver was organized to point out this connection. At three global conferences of activists and decision-makers from around the world — in London in 2007, in Washington, D.C. in 2010 and in Kuala Lumpur in 2013 — it provided statistics and case studies that proved the truth of its slogan, “Invest in women — it pays!” Every year brought more proof and better examples of investments in girls and women in which everybody won. So today, as the international community begins final MDG assessments and considers future plans, we are proud to announce that the next triennial Women Deliver conference will be held on May 17-19, 2016 in Copenhagen, Denmark.
Like the previous three gatherings, this one will bring together advocates, policymakers, journalists, young people, researchers and leaders of the private sector and civil society to showcase what it means and how it works when women and girls become the focus of development efforts. It will document the great results around the world where investment in women rose.
The Women Deliver 2016 Conference will also be the first major global conference after the post-2015 development framework, so far called the Sustainable Development Goals, is decided. It will be a first chance for strategizing on ways to turn the MDG spurs for growth into the plowshares of a livable planet, to make startup programs sustainable over the long term, to bring pilot programs to national scale — in short, to firm up long-term support, ensure that girls and women are kept at the center of the new development plans from the beginning, and include them in operations and evaluations at every stage into the future.
Copenhagen was chosen because Denmark is a leader and champion for progress in sexual and reproductive health and rights. The Danish International Development Agency has already launched a new Strategic Framework for Gender Equality, Rights and Diversity to assist women and girls in seizing opportunities and resources to take full control over their own lives. The Ministry of Foreign Affairs of Denmark is fully in support of Women Deliver’s call for additional global commitment on behalf of girls and women.
The post-2015 development framework is being developed as we write, and Women Deliver is working to ensure that decision makers prioritize maternal, sexual and reproductive health and rights, especially in countries where inequality prevails and where it would help development most.
Closing the gender gap in agriculture alone, for example, could lift up to 150 million people out of hunger. Investing $8.1 billion a year in voluntary family planning would reduce pregnancy-related deaths by 79,000 and newborn deaths by 1.1 million every year. Increasing girls’ school attendance by only 10 percent raises a country’s GDP by 3 percent. And eliminating barriers to employment for girls and women could raise labor productivity in some countries by 25 percent.
These are the facts of life in the 21st century. Imagine a world where no woman dies giving life, where no baby is born with HIV, where every girl can attend school and get a quality education, and where everybody has a chance to fulfill their potential. The post-2015 process can move us closer to that day — if it prioritizes the health, rights, and well-being of girls and women.
In these last 500 days, Women Deliver will build on the momentum generated by our previous gatherings to see that it happens. We will insist that adolescents and young people, who predominate in most developing areas, should get special focus. We will make sure that women are present at the tables where decisions are made. And we will continue playing a critical role in fueling the global movement for maternal, sexual and reproductive health and rights.
We will see you all in Copenhagen!
Aug. 18, 2014, marks the 500-day milestone until the target date to achieve the Millennium Development Goals. Join Devex, in partnership with the United Nations Foundation, to raise awareness of the progress made through the MDGs and to rally to continue the momentum. Check out our Storify page and tweet us using #MDGmomentum.
By Jill Sheffield and Katja Iversen
18 August 2014
Source: https://www.devex.com/news/500-days-and-counting-progress-for-girls-and-women-means-progress-for-all-84064
During the 2014 International AIDS conference, The Lancet medical journal released a series of articles focused exclusively on HIV and sex work. One study by Kate Shannon et al., demonstrates that decriminalization of sex work could reduce HIV infections by 33 to 46 percent over the next decade. Shannon’s team showed that “multi-pronged structural and community-led interventions” are essential to promoting the human rights of sex workers, as well as improving their access to HIV prevention and treatment. Dr. Chris Beyrer, the researcher who coordinated this Lancet series, told AIDS conference participants that“[e]fforts to improve HIV prevention and treatment by and for people who sell sex can no longer be seen as peripheral to the achievement of universal access to HIV services and to eventual control of the pandemic,” drawing an irrefutable line between the social, legal, and economic injustices sex workers face and their subsequent vulnerability to HIV.
The Lancet series authors join many other prominent public health voices in identifying the decriminalization of sex work as vital to preventing the spread of human immunodeficiency virus (HIV) and of acquired immune deficiency syndrome (AIDS). For two decades, sex workers rights’ activists throughout the world have pushed human rights, public health, and HIV and AIDS response leaders to recognize that they, along with people who inject drugs and men who have sex with men, are “key populations” without whom an effective HIV and AIDS response is impossible. In 2012, the World Health Organization (WHO) declared that “all countries should work toward decriminalization of sex work and elimination of the unjust application of non-criminal laws and regulations against sex workers.” In South Africa (with the largest population of people living with HIV in the world), the National AIDS Council is urging its government to decriminalize sex work—a demand that advocates and health policy professionals are making in dozens of other countries as well. Amnesty International, Human Rights Watch, and the UN’s Global Commission on HIV and the Law all endorse this position. The latter points out “the impossibility of governments stigmatizing people on one hand, while simultaneously actually helping to reduce their risk of HIV transmission or exposure on the other.”
Sex work has been decriminalized in New Zealand and one province (New South Wales) in Australia leaving sex work businesses subject to standard occupational health and safety regulations. Law enforcement treats the sale of sex as it does any other business, without any intrusion or interruption unless existing laws are being violated.
Decriminalization has resulted in higher rates of condom use and enables sex workers to organize community-based health practices that demonstrably improve health and reduce HIV risk. It also makes it possible for sex workers to report and for the police to address illegal acts as they occur, such as assault, theft of services, employment of minors, or client coercion. In this decriminalized setting, sex workers can be strong allies in the fight against trafficking, intimate partner violence, and child abuse since they can report incidents to the police and social service agencies without putting themselves at risk of arrest.
So, why is the HIV-AIDS field only just beginning to recognize the connection between the decriminalization of sex work and HIV? And why is the trend toward criminalizing populations involved in the sex trades increasing in the United States—moving in the opposite direction from other countries? The following are three contributing factors.
Public debate around sex work in the United States increasingly focuses on people who have been trafficked or otherwise coerced into the sex trade. Anti-trafficking advocates conflate sex work (people choosing to sell sexual services from among employment options available to them) with trafficking (people being forced into the sex industry against their will). Laws that criminalize all people selling sex (voluntarily or involuntarily) violate the rights of the former and undermine efforts to identify and assist the latter. The Global Commission on HIV and the Law states unequivocally that, “Sex work and sex trafficking are not the same. The difference is that the former is consensual, whereas the latter is coercive.”
A commentary by Steen et al. in the recent Lancet series notes that “repressive and counterproductive police action,” including the arrest and incarceration of trafficking victims for the purposes of “rescue,” has overtaken far more effective responses in several countries. The understandable, but destructively over-simplified, mandate to “rescue and restore” sex workers is also being imposed in public health settings where providers are now charged with identifying and intervening with potential victims of trafficking in the sex trade. Certainly, health-care providers have a duty to watch for and help patients in abusive situations of all kinds. They also have a duty to understand the complexities of human experience, respond to patient-identified needs, and maintain that patients are experts of their own lives, whatever that may look like.
Providing access to health-care services targeted to consumers’ needs is a vital part of any country’s HIV response. Without it, those most in need of prevention, care, and treatment are least likely to get it.
In a 2010 survey, 53 percent of medical students said they were not adequately trained to address their patients’ sexual issues comfortably. Far fewer professional medical curricula explicitly prepare students to understand that they will encounter sex workers as patients who, like all other patients, are individuals with a wide range of experiences, backgrounds, and needs that can best be treated with patient-centered care.
When sex workers receive demeaning and unprofessional treatment in health-care settings, they see health-care providers as an extension of the larger system that criminalizes them. A survey by the New York City-based Persist Health Project found that few sex workers disclosed their occupation to their health-care provider; only one study participant reported a positive experience after doing so. As one respondent explained, “I think for security reasons, I don’t usually disclose. Mainly because I don’t trust doctors … I sort of treat them like law enforcement.” Another noted that most health-care providers “have no clue who you are, no clue about your background, you can’t read them or know that they’re not going to try to lecture you or give you a stink-eye.”
St. James Infirmary, a peer-based occupational safety and health clinic for sex workers in San Francisco, corroborates these findings. Of their incoming patients, 70 percent had never previously disclosed their occupation to a medical provider for feared of bad treatment. Providing sex-worker friendly health care requires training health-care workers appropriately and supporting services designed specifically with and for the communities they serve.
People usually envision a sex worker as someone soliciting on the street, but only about 20 percent of U.S. sex workers are street-based. The vast majority see clients in other venues including massage parlors, brothels, apartments they share with other sex workers, or a client’s hotel room. Many connect with clients online.
HIV risk is high among street-based sex workers who experience high levels of violence at the hands of clients and abusive law enforcement personnel. One important way they reduce this risk is assessing a potential client before getting into his car—looking for signals that he might be violent and relaying his license number to a colleague in case the worker disappears. This assessment time is also used to negotiate price and condom use. Law enforcement crack-downs compel sex workers to complete their negotiations quickly (in order to avoid arrest), depriving them of the time needed for assessment and negotiation.
Street-based sex workers have little or no protection if a client becomes violent or refuses to use a condom. Of the street-based workers surveyed in The Lancet study by Shannon et al., 25 percent reported being pressured by clients to have sex without a condom. Those working in remote areas (such as industrial parks) to escape local policing were three times more likely to report being pressured into having sex without a condom than the study population overall. The recent Lancet series data also shows that, in some countries, up to one-third of sex workers do not carry an adequate supply of condoms due to “condoms as evidence” policies that allow police to seize a sex worker’s condom supply and use it as evidence of their intent to engaged in sex work—a widely-used policy in several U.S. cities.
Punitive laws against sex work are in place in 116 countries, including the United States, creating, according to the Open Society Foundations, “a state-sanctioned culture of stigma, discrimination, exploitation, and police and client violence against sex workers.”
Decriminalizing sex work in the United States is a long and challenging process, but there is a path to follow. The 1988 ban on federal funding for syringe exchange remained in place for 20 years and, after briefly lifting it in 2009, the Obama administration agreed to its reinstatement in 2011 at Congress’ insistence. Advocacy pressure to overturn it continues.
Thanks to the efforts of dedicated researchers and activists during the two decades between 1988-2009, public health professionals, medical institutions and virtually everyone working in the HIV-AIDS field learned why harm reduction practices are essential. Services to people who use drugs began to improve, although they are still inadequate, primarily because they are grossly under-funded. Progress has been made.
The U.S. National Institutes of Health (NIH) issued a consensus statement that addressed the need for syringe exchange but also observed that “[p]rograms targeting sex workers have been highly efficacious in other countries, but [in the U.S., programs] will encounter cultural and political barriers.” The public silence maintained on this issue for the last 17 years is emblematic of those barriers.
But sex workers’ rights organizations in most U.S. cities, though heavily marginalized, have not been silent. They are struggling to end “condoms as evidence” practices, train health-care providers, find or establish sex worker-friendly health-care services, and demand their rightful place as invaluable allies in ending human trafficking and preventing the spread of HIV. Like the harm reductionists who set up the first syringe exchange sites in the United States, they need the support of mainstream sexual and reproductive health advocates willing to learn from them and join them. Like the early harm reductionists, they need the rest of us to bring our money, skills, and political support this human rights struggle.
We can’t stop HIV in the United States without sustainable and long-term solutions to end the arrest, detention, and incarceration of sex workers in the United States, as well as end the violations against sex workers within the correctional system. A meta-analysis of more than 800 other studies and reports, published in the recent Lancet series, listed abuse experienced by sex workers as including “homicide; physical and sexual violence, from law enforcement, clients, and intimate partners; unlawful arrest and detention; discrimination in accessing health services; and forced HIV testing.” It added “protection of sex workers is essential to respect, protect, and meet their human rights, and to improve their health and well-being.”
Expert voices in support of community-led, sex worker-centered health care in the fight against HIV are becoming more and more numerous. When will the mainstream HIV and AIDS organizations and women’s health advocacy communities join loudly in this demand?
by Anna Forbes and Sarah Elspeth Patterson
13 August 2014
Source: http://rhrealitycheck.org/article/2014/08/13/evidence-decriminalizing-sex-work-critical-public-health/
The UN predicts that two-thirds of the world will live in cities by 2050, with 90% of growth taking place in the global south

Two-thirds of the world's population will live in cities by 2050, posing unique infrastructural challenges for African and Asian countries, where 90% of the growth is predicted to take place.
The planet's urban population – which overtook the number of rural residents in 2010 – is likely to rise by about 2.5 billion to more than 6 billion people in less than 40 years, according to a UN report. Africa and Asia "will face numerous challenges in meeting the needs of their growing urban populations, including for housing, infrastructure, transportation, energy and employment, as well as for basic services such as education and healthcare", it adds.
Future development targets should focus on creating inclusive cities with adequate infrastructure and services for all residents, said John Wilmoth, director of the UN's population division. "Managing urban areas has become one of the most important development challenges of the 21st century," he said. "Our success or failure in building sustainable cities will be a major factor in the success of the post-2015 UN development agenda."
The report says rapid urbanisation will bring opportunities for governments to improve access to important services. "Providing public transportation, as well as housing, electricity, water and sanitation for a densely settled population is typically cheaper and less environmentally damaging than providing a similar level of services to a predominantly rural household," it says.
Africa is projected to experience a 16% rise in its urban population by 2050 – making it the most rapidly urbanising region on the planet – as the number of people living in its cities soars to 56%.
The report predicts there will be more than 40 megacities worldwide by 2050,each with a population of at least 10 million. Delhi, Shanghai and Tokyo are predicted to remain the world's most populous cities in 2030, when each is projected to be home to more than 30 million people.
"Several decades ago most of the world's largest urban agglomerations were found in the more developed regions, but today's large cities are concentrated in the global south," the UN says. "The fastest growing urban agglomerations are medium-sized cities and cities with fewer than 1 million inhabitants, located in Asia and Africa."
The world's 3.4 billion-strong rural population will start to decline as urbanisation becomes more common, the report says. The UN projects that rural populations will increase in only a third of countries between 2014 and 2050, as states with large rural communities will take longer to urbanise. "In general, the pace of urbanisation tends to slow down as a population becomes more urbanised," the report says.
The UN cautions that sustainable urbanisation requires cities to generate better income and employment opportunities, and "expand the necessary infrastructure for water and sanitation, energy, transportation, information and communications; ensure equal access to services; reduce the number of people living in slums; and preserve the natural assets within the city and surrounding areas".
Urbanisation has historically taken place in wealthy countries, but such expansion is now happening most rapidly in upper-middle-income countries, where gross national income per capita is between $1,046 and $4,125.
Source: http://www.theguardian.com/global-development/2014/jul/10/urban-population-growth-africa-asia-united-nations

The latest version of the zero draft report from the Open Working Group developing the Sustainable Development Goals (SDGs) hit the internet late Monday evening. This is the final draft that member states will have a chance to respond to before the final report is produced and shared with the Secretary General prior to the United Nations General Assembly in September. It is fairly similar to the last draft in that it still has the same 17 goals, with small semantic differences. Overall, there are fewer targets, but both the targets and the process are becoming increasingly convoluted.
This draft misses the integration, aspiration, transformation and sustainability that were meant to drive the post-2015 agenda. We see important targets missing in this lengthy draft, but we have yet to really see the difficult trade-offs that a final set of implementable goals would require.
Sexual and reproductive health has disappeared from the Health Goal. While a target on sexual and reproductive health was previously included under both the Health and Gender goals, it now only appears under the Gender goal as “ensure universal access to sexual and reproductive health and reproductive rights in accordance with the Programme of Action of the ICPD and the Beijing Platform for Action.” This is problematic for two reasons:
1. Without SRH under the health goal, family planning is in jeopardy of not being recognized in this new development framework. SRHR is a major component of overall health not only for women and girls, but also for men and boys. It is therefore critical to be included within a discussion of health.
2. The qualifier of ICPD and Beijing is unnecessary and weakens the human rights frame of the target. Nowhere else in the Open Working Group’s draft document is such a caveat introduced. As such, it undermines the principle of arriving at a forward-looking set of SDGs. There is no need to qualify universal access to sexual and reproductive health or reproductive rights. With a reference to ICPD and Beijing already in the introduction, we hope to see this qualifier removed.
In New York for the Open Working Group session last week, you could see will, desire, and investment on the faces of delegates, civil society, co-chairs. But you could also see the fatigue. This has been a long and intensive exercise that has lasted nearly two years already. Now is the time point to put words down on paper and respond to drafts in order to rescue the jumbled mess that the draft goals have become.
The final round of informal discussions by the Open Working Group takes place July 14 to 18. The co-chairs (from Kenya and Hungary) will incorporate this final feedback from member states into a final report submitted to the Secretary General in August. A report will simultaneously be submitted by the Intergovernmental Committee of Experts on Sustainable Development Financing. The Secretary General will then take these inputs, among others, and produce his own report, and full negotiations are expected to start in January 2015. The co-chairs of the post-2015 summit (September 21 to 23) are Denmark and Papua New Guinea.
By A. Tianna Scozzaro, Population and Climate Associate –
3 July 2014
Source: http://www.populationaction.org/blog/2014/07/03/post-2015-agenda-organized-chaos-or-hot-mess/#sthash.VKfcdhBU.dpuf
There is a risk that Millennium Development Goals aimed at improving child and maternal mortality and expanding access to sanitation will be missed, the United Nations has warned.
With a little over a year to go to ensure the eight MDG targets are met, the UN this week issued a progress report, which showed that goals on poverty reduction, improving drinking water sources, improving the lives of slum dwellers and achieving gender parity in primary schools had already been met.
Progress was also being made on MDGs covering hunger, debt relief and malaria, tuberculosis and HIV treatment.
‘However, some MDG targets related to largely preventable problems with available solutions, such as reducing child and maternal mortality and increasing access to sanitation, are slipping away from achievement by 2015, despite major progress,’ the UN said.
‘The report calls on all stakeholders to focus and intensify efforts on the areas where advances have been too slow or not reached all.’
More reliable statistics were needed for monitoring development, the report said. It noted that the number of member states submitting progress reports on HIV/Aids increased from 102 in 2004 to 186 in 2012, helping galavanise global efforts. Funding for HIV programmes more than tripled in this period and 9.5 million people living with HIV were accessing antiretroviral treatment in 2012.
UN member states are currently considering a new set of development goals that can replace the MDGs in 2015. These are likely to be agreed in September next year.
UN secretary general Ban-Ki Moon said: ‘Our efforts to achieve the MDGs are critical to building a solid foundation for development beyond 2015. At the same time, we must aim for a strong successor framework to attend to unfinished business and address areas not covered by the eight MDGs.
‘Tackling growing inequality, in rich and poor countries alike, has become the defining challenges of our times. Our post-2015 objectives must be to leave no one behind.’
By Vivienne Russell
9 July 2014
http://www.publicfinanceinternational.org/news/2014/07/un-warns-some-mdg-targets-may-be-missed/

United Nations: India continues to battle poverty, child and maternal deaths, according to a United Nations report on the Millennium Development Goals that said while several key global targets have been met, more sustained effort is needed to cover disparities by the 2015 deadline.
The 'Millennium Development Goals Report 2014', launched by UN Secretary-General Ban Ki-moon here yesterday, said many global MDG targets on reducing poverty, increasing access to improved drinking water sources, improving the lives of slum dwellers and achieving gender parity in primary schools have already been met.
Many more goals are within reach by their 2015 target date, the report said, adding that if current trends continue, the world will surpass MDG targets on malaria, tuberculosis and access to HIV treatment.
The report is the most up-to-date "global scorecard" on efforts to achieve the eight mostly anti-poverty goals agreed by world leaders at a UN summit in 2000.
It, however, said that some MDG targets related to largely preventable problems with available solutions, such as reducing child and maternal mortality and increasing access to sanitation, are slipping away from achievement by 2015, despite major progress.
"We know that achievements have been uneven between goals, among and within regions and countries, and between population groups," Ban said, adding that unless imbalances are addressed through bolder and more focused interventions, some targets will not be met, including in key areas such as childbirth, maternal mortality, universal education, and environmental sustainability.
The overwhelming majority of people living on less than 1.25 dollars a day belong to Southern Asia and sub-Saharan Africa, with one third of the world's 1.2 billion extreme poor living in India alone in 2010.
While Southern Asia has made "strong and steady" progress in reducing child deaths by more than halving its under-five mortality rate, yet nearly one in every three deaths still takes place in the region.India also had the highest number of under-five deaths in the world in 2012, with 1.4 million children dying before reaching their fifth birthday.
Despite progress in all world regions, the maternal mortality ratio in developing regions ? 230 maternal deaths per 1,00,000 live births in 2013 ? was 14 times higher than that of developed regions, which recorded only 16 maternal deaths per 1,00,000 live births in 2013.
Highlighting the extreme differences in maternal mortality among countries, the report said that almost one-third of all global maternal deaths are concentrated in the two populous countries – India and Nigeria.
India has an estimated 50,000 maternal deaths (17 per cent) while Nigeria has an estimated 40,000 maternal deaths (14 per cent).
The report further stated that despite a large increase in sanitation coverage, with an additional two billion people gaining access to an improved sanitation facility, it seems unlikely that the MDG target of 75 per cent coverage will be met by 2015.
"In 2012, a billion people still resorted to open defecation, a practice that needs to be brought to an end, as it poses a huge risk to communities that are often poor and vulnerable already," the report added.
"Open defecation is most prevalent in Southern Asia, Oceania and sub-Saharan Africa. The vast majority ? 82 per cent ? of people practicing open defecation now live in middle-income, populous countries, such as India and Nigeria," it said, adding that nearly 60 per cent of the one billion people practicing open defecation live in India.
With the 2015 deadline for achieving the landmark goals less that 550 days away, the report said many of MDGs have been met or are within reach. Among the targets that have been met is that the world has reduced extreme poverty by half.
In 1990, almost half of the population in developing regions lived on less than 1.25 dollars a day. This rate dropped to 22 per cent by 2010, reducing the number of people living in extreme poverty by 700 million.
Efforts in the fight against malaria and tuberculosis have shown results with an estimated 3.3 million deaths from malaria being averted between 2000 and 2012 due to the substantial expansion of malaria interventions.
The intensive efforts to fight tuberculosis have saved an estimated 22 million lives worldwide since 1995.
"If the trends continue, the world will reach the MDG targets on malaria and tuberculosis," it said.
Access to an improved drinking water source became a reality for 2.3 billion people and the target of halving the proportion of people without access to an improved drinking water source was achieved in 2010, five years ahead of schedule.
In 2012, 89 per cent of the world's population had access to an improved source, up from 76 per cent in 1990.
Hunger also continues to decline, but immediate additional efforts are needed to reach the MDG target, the report said.
The proportion of undernourished people in developing regions decreased from 24 per cent in 1990?1992 to 14 per cent in 2011?2013. However, progress has slowed down in the past decade.
"Meeting the target of halving the percentage of people suffering from hunger by 2015 will require immediate additional effort, especially in countries which have made little headway, the report added.
Launching the final push towards the United Nations targets, Ban appealed to member states that the global post-2015 objective must be to "leave no one behind".
Ban said the world is "at a historic juncture, with several milestones before us."
Citing gains made in the fight against malaria and tuberculosis and access to HIV treatment, Ban underscored that the report makes clear "the MDGs have helped unite, inspire and transform…And the combined action of Governments, the international community civil society and the private sector can make a difference."
"Our efforts to achieve the MDGs are critical to building a solid foundation for development beyond 2015. At the same time, we must aim for a strong successor framework to attend to unfinished business and address areas not covered by the eight MDGs," said the UN chief.
PTI
First Published: Tuesday, July 08, 2014, 08:44
Source: http://zeenews.india.com/news/health/health-news/poverty-child-maternal-deaths-high-in-india-un-report_28670.html