

Category Archives: Capacity building

Malawi develops civil society charter to tackle HIV and TB.

Malawi 3

On 13 February, civil society organisations and partners met in Malawi met to develop a civil society priorities charter in the response to HIV and TB.


Aids Accountability International convened the workshop in the capital Lilongwe, which included representatives from the Global Fund to Fight AIDS, Tuberculosis and Malaria.


Victor Chayamba, executive director of Malawi Global Fund Coordinating Commitee (MGFCC), said: “Civil society is an integral part of the Global Fund grant architecture. However, over the years, there has been little or no opportunity for the sector to come together and define a set of interventions to advocate for inclusion in funding proposals.”


Limited access to funding


Civil society organisations (CSO) often feel they are not being consulted in the process of defining programmes to be included in Global Fund proposals. As a result they often fail to properly position themselves to receive grants.


In the past only a few well-established and city-based civil society organisations were involved in the process. Chayamba said: “At best, they would manage to fight for inclusion of just a fraction of the sector’s requirement and at worst they would advance their own agendas to the detriment of the common good.”


According to Chayamba this effectively meant some sections of society were denied access to services which would otherwise be provided by these CSOs.


“This put the MGFCC in an awkward position as explanations were always sought on why there was inadequate input from the sector. All that will now be a thing of the past with the development of the Civil Society Priorities Charter,” said Chayamba.


Civil society priorities


Through the charter, civil society will have an opportunity to speak with one voice to express priorities to be included in applications via the Global Fund’s New Funding Model.


The process enables civil society to think strategically about what can and should be supported bearing in mind the sector’s comparative advantage. It also enhances a shared responsibility towards service delivery for the benefit of local people.


Malawi is the third country to develop a civil society priorities charter at this critical time in the process for developing its response to HIV and TB.


A vote by Civil Society Organizations present during the workshop showed that changing people’s behaviour, for example in the use of condoms, and focusing on key populations, such as injecting drug users, men who have sex with men and sex workers, are their top priorities.


Read more about HIV and the key players


Image: In Malawi, where AIDS remains the leading cause of death, the Alliance has been supporting a pioneering programme where volunteers refer people in their community to formal health services and community based organizations for support.
© International HIV/AIDS Alliance


By Owen Nyaka

25 February 2014

Source: http://www.keycorrespondents.org/2014/02/25/malawi-develops-civil-society-charter-to-tackle-hiv-and-tb/

Ethiopian Minister Slams Uganda for Passing Anti-Gay Law.

2014-02-25-ZenebuTadesse.jpg

Addis Ababa, Ethiopia — Zenebu Tadesse, Ethiopia's Minister of Women, Children and Youth Affairs has taken to twitter criticizing the passing of Uganda's anti-gay law, on Monday.

Tadesse tweeted: "There is no place for hate, discrimination in my beloved Africa. It's not Governments' business to make dress code or anti-gay laws #Uganda."

The tweet came shortly after Ugandan President Yoweri Museveni signed a harsh anti-gay law that punishes gay sex with up to life in prison.

Tadesse's African voice joins a worldwide condemnation of Uganda's new anti-gay law.

On Sunday, the former Archbishop of Cape Town, Nobel Peace Prize winning Desmond Tutu has compared Uganda's new anti-gay law to Nazi and Apartheid discrimination.

Reacting to the news, Ugandan LGBT rights advocate, Frank Mugisha, told me that he very much welcomed Tadesse's statement.

He said: "this will help. We need as many possible African voices speaking against this law."

While activist Melanie Nathan, a native of South African commented: "This is hugely significant statement coming from an accomplished and respected African Minister.

"I believe that many more Africans of noble esteem probably believe that which she has had the courage to speak," asking others to show equal courage and follow her lead.

Nathan added that she is "especially disappointed that we have yet to hear officially from South Africa's President Zuma, from the only country in Africa where there is a fully equal constitution."

She said he should follow Nelson Mandela's legacy and Tadesse's lead.

Ethiopia has already a harsh anti-gay law which punish same-sex acts with up to 15 years imprisonment.

In addition, under its anti-terrorism law anyone who states what the government deems terrorism (which can include human rights criticism) can be imprisoned for 20 years, without a warrant.

Ethiopia's anti-advocacy law bars charities and nongovernmental organizations that receive more than 10 percent of their funding from abroad from participating in activities that advance human rights and the promotion of equality.

Essentially these three laws taken in total make it impossible for any health-services, charity, advocacy or even clubs or bars to openly support or cater for Ethiopia's LGBT population.

Like in Uganda a strong Evangelical lobby along with other religious leaders have been campaigning for an even tougher capital punishment against LGBT Ethiopians.

Mercy (pseudonym to protect his identity), director of the underground Rainbow Ethiopia, a health and support group for Ethiopian LGBT people, told me he welcomed Tadesse's statement, which he called "progressive."

He also stated: "But I'd like to ask her thought about the draconian anti-homosexuality law, the lack/denial of health and social services and harassment/torture of LGBT Human rights defenders in Ethiopia."

By Dan Littauer

25 February 2014

Source: http://www.huffingtonpost.co.uk/dan-littauer/uganda-anti-gay-law_b_4851882.html

Keep Calm: African CSO Post 2015 Coalition Advocacy Strategy Meeting.

AIDS Accountability International Africa CSO Coalition Post 2015 10AIDS Accountability International Africa CSO Coalition Post 2015 6


The International Conference on Population and Development, Commission on the Status of Women and the Post 2015 Development Agenda review processes are all important opportunities for African civil society to influence the future development agenda.


In the Africa review process of the ICPD, SDGs and CSW (that resulted in several continental positions on the post 2015 development agenda) it became clear that is civil society requires better collective organization and strategizing to perform effective advocacy. This needs to happen both at country and regional level so as to ensure the greater inclusion of Sexual Reproductive Health and Rights (SRHR) in the outcomes of these processes.


Countries will be committing to their new positions in New York (NYC) this year and the sole remaining opportunity available to civil society is to affect the position of each African country prior to their vote.


As a means to affect these country positions AAI will be leading the African CSO Post 2015 Coalition which is intended to ensure that African civil society works strategically for the best outcomes. We will thus be holding a meeting in Johannesburg in March/April (date to be confirmed) that will map out the position of countries in Africa with regard to their position on SRHR, and we will plan as a group how we can affect the outcomes in NYC.


We are looking for a particular set of people at this meeting, so if think you fit the criteria, or know someone who does, nominate them to nomvuyo@aidsaccountability.org Read more about the meeting, and the criteria click here.

Southern Africa: Zambia and Swaziland Develop Roadmap to Change Behavior in Response to HIV

keycorrespondents180Two southern Africa countries with high rates of HIV have developed advocacy roadmaps to ensure campaigns to change behavior are central to their countries' fight against AIDS.

Both Swaziland and Zambia developed Civil Society Charters in late 2013 as part of their proposal for grants from the Global Fund to Fight AIDS, Tuberculosis and Malaria. South Africa, Malawi and Namibia are expected to do the same in early 2014 ahead of their planned submissions of concept notes to the Global Fund.

Civil society leaders in Swaziland and Zambia told Aidspan – independent observers of the Global Fund – that activities to change behavior will be critical priorities for HIV concept notes, which is a change from previous grant proposals that emphasized treatment and care over prevention activities.

Success in Zambia

Zambia has used cost-sensitive behavior change activities to great effect in its efforts towards reducing new HIV infections.

"At Treatment Advocacy and Literacy Campaign (TALC), we have been addressing these key social factors that contribute to high prevalence of HIV," said Felix Mwanza, the Zambia-based organization's director. "We have been doing this by sensitizing communities on the importance of having one partner and using condoms."

Multiple and concurrent partnerships combined with low levels of condom use are driving the prevalence rate in Zambia, currently estimated at 12.7% among adults aged 15-49.

Programs envisioned by the civil society organisations will target schools, places of worship and mining areas and are likely to emphasize condom use.

Community ownership in Swaziland

For civil society organisations in Swaziland, community ownership and sustainability of programming beyond the life of externally funded projects is critical. By targeting the youth, especially girls, it is hoped that behavior change campaigns will be rooted in their communities, allowing for long-term sustainability beyond the life of any external funding.

Campaigns encouraging condom use will be rolled out from April in urban areas, with schools, popular night spots, soccer pitches and bus depots the primary targets.

Some 210,000 people in Swaziland, or 26.5% of adults aged 15 to 49, are infected with HIV.

Working with key populations affected by HIV

AIDS Accountability International senior researcher Dr Gemma Oberth said getting the health needs of key populations on the agenda is still a challenge in Southern Africa.

"It is encouraging to see Swazi civil society prioritizing access to services for LGBT [lesbian, gay, bisexual and transgender] fairly high on their list," Dr. Oberth said.

"It is also a good sign that Zambian civil society understands key populations to be a cross-cutting issue, prioritizing LGBT individuals as target populations under their priorities for condom promotion as well as treatment, care and support."

This story was first published by Aidspan on 6 February 2014

Malawi: Joyce Banda Forms Education Committee.

President-Banda

Blantyre — As one way of showing commitment towards the protection of a girl child in the country President Dr Joyce Banda has established a Special Committee on the Acceleration of Girls Education in Malawi.

The President disclosed this on Thursday at Sanjika Palace during an audience with High Level Task Force for Women, Girls, Gender Equality and HIV for Eastern and Southern Africa saying this committee will look at how to overcome traditional barriers to girls' education, such as early marriages and pregnancies.

The Head of State then called upon relevant authorities to hold the necessary consultations and lobbying to ensure that the country attain the right to support for the age of marriage in Malawi to be raised to at least 18 years for both boys and girls to give them time to acquire enough education before marriage.

"There is no question about my personal commitment to the raising of the marriage age. I am however aware that this is a delicate issue among some traditional leaders, conservative communities, faith leaders and some legislators.

"That is why, in my opinion, it is best that we do our homework by engaging all stakeholders and bring the bill to parliament at the right time for us to succeed," said the President Banda.

The president highlighted that there is so much that the country can achieve through working with traditional leaders who are guardians of traditional culture. She said the T/A's ability to mobilise support within their communities will be crucial in promoting and protecting girl child at a local level.

The president said she was very pleased to learn that some chiefs have already started taking big strides in promoting the girl child through the creation of a Declaration of Commitment to be signed by Paramount and Senior Chiefs.

"This declaration focuses on issues of the girl child in a holistic way, looking at education, gender-based violence, sexual and reproductive health and rights, early marriages, and HIV, while also taking advantage of the positive aspects of our culture and cultural ceremonies to support these efforts," delighted the head of state.

In her remarks leader of the High Level Task Force for Women, Girls, Gender Equality and HIV for Eastern and Southern delegation, Professor Sheila Tlou who is UNAIDS Regional Director commended President Dr Joyce Banda for her efforts in improving the welfare of the girl child education and her continued support to girls' education.

She however requested for the formation of a high level committee which will oversee the enactment of the marriage bill so that more girls should be able to complete their education before marriage.

BY YAMIKANI YAPUWA

1 NOVEMBER 2013

http://allafrica.com/stories/201311030198.html


For Millions of Adolescents, Pregnancy Can Be Dangerous.


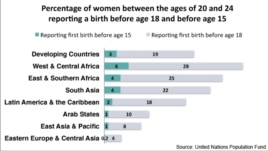
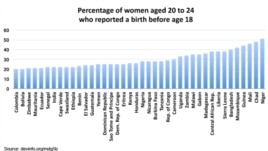
GENEVA — A new report by the United Nations Population Fund (UNFPA)finds millions of adolescent girls suffer serious long-term health and social consequences from pregnancy.  Globally, the U.N. agency estimates 7.3 million girls under 18-years-old give birth, including two million girls younger than 14.
Giving birth to a baby should be a happy moment in the life of a woman.  But, for millions of adolescents around the world, early pregnancy and childbirth results in serious health problems, social exclusion and even death.

In developing countries, 20,000 girls under 18 give birth every day, the report says.  It estimates some 70,000 adolescents in developing countries die each year from complications during pregnancy and childbirth.  Among those who survive, many will develop an obstetric fistula. This is a hole in the birth canal, which leaves the girl leaking urine constantly.

The director of the UNFPA office in Geneva, Alanna Armitage, says adolescent girls are at increased risk of child marriage and sexual coercion.  Maternal death among girls under the age of 15 from low- and middle-income countries is twice that of older females,” says Armitage.

“Our report shows that nine out of 10 pregnancies to girls under 18 take place within a marriage. And, as you may know, every day, 39,000 girls are married in violation of their basic human rights.  One in nine is married before the age of 15 and this, of course, will continue as long as families, communities and governments tolerate child marriage,” she said.

The report highlights the economic impact of adolescent pregnancy.  It notes the lifetime opportunity costs related to adolescent pregnancy range from one percent of annual GDP in China to 30 percent of annual GDP in Uganda.

To drive this point home, the report notes $3.4 billion could have been added to the Kenyan economy had the more than 200,000 adolescent mothers in the country been employed rather than pregnant.

The report finds in every region of the world, impoverished, poorly educated rural girls are more likely to become pregnant than those who live in richer, more urban areas.  UNFPA Senior Maternal Health Advisor Luc de Bernis says the highest rates of adolescent maternal mortality are found in Sub-Saharan Africa and South Asia.

He says the problem is marginally greater in the Francophone than the English-speaking African countries.

“Africa is not homogeneous and we have many differences, but the fact is young girls are not protected in the majority of these countries — not in the Francophone for sure…and not in the English speaking world,” said Bernis. “In Kenya, Uganda, you have a rate of abortion which is absolutely enormous and it explains a big part of the maternal mortality.  A big number of these abortions occur among very young girls.”

The report says adolescent pregnancy is a much bigger challenge in the developing world than in developed countries.  But it finds that adolescent pregnancy is still a significant issue in the richer nations.

It says blaming a young girl for getting pregnant is counter-productive.  Instead of changing the girl’s behavior, the report says, society should change its attitudes and actions.

Among the recommendations for reducing adolescent pregnancy with its related risks, the report suggests keeping girls in school, stopping child marriage, and providing adolescents with access to sexual and reproductive health, including contraception.

By Lisa Schlein

30 October 2013

http://www.voanews.com/content/pregnancy-dangerous-for-millions-of-adolescents/1780067.html

Put Young Girls at the Centre of Development

Do you remember your favorite toy as a child? Your first day at school? Your first love? The moment you clearly felt you’d become an adult?

Many young girls will never have any of those memories. As of today, the International Day of the Girl Child, around 250million of them live on less than $2 a day. They don’t go to school. They’ve never seen a doctor. In many cases, they’re married before they turn 15 and many die from childbirth complications.

Adolescent girls are not children, but they’re not quite adults. That makes them particularly vulnerable, powerless and at risk of different forms of exploitation. They are a category on their own, with very specific needs that global policy makers and the international humanitarian community must identify, understand and tackle appropriately.

So far, this hasn’t happened. Adolescent girls have notably been left out of the Millennium Development Goals agenda which, while successfully targeting the improvement of healthcare standards for women and children, has failed to address crucial issues regarding teenagers. In the eyes of those driving development, an adolescent girl is invisible.

There are plenty of ‘invisible girls’ around the word: 50% of Tanzania’s population is under the age of 15; 30% of the demographic of the entire Middle East is between the age of 15 and 29; and in India, more than half the nation is under 25. This is the largest youth generation in history. Its potential is unrivalled, yet left completely untapped. Worst, this category is now at risk.

Very rarely is contraceptive promotion targeted to the specific needs of young girls. Standard family planning for adult women is implemented instead. The unfortunate result is a rise in HIV infections and sexually transmitted diseases, along with 86million unintended pregnancies, almost half of which lead to abortion. Three million of such abortions are unsafe, and are a leading cause of maternal mortality.

Nearly 10% of all girls in low-income countries are mothers before they turn 16. They are five times more likely to die in childbirth than women aged 20; their bodies are just not ready for pregnancy. Yet in African countries – where half of all births are to adolescent girls – sexual and reproductive health services tend to focus exclusively on married women.

Violence against girls continues to be one of the most pressing challenges the world faces. Nearly half of all recorded sexual assaults worldwide are against girls aged 15 or younger, but very little has been done by the international community to create the right framework for these young victims to come forward, so justice can be enforced. As a result, the vast majority of violent crimes against girls go completely unreported.

How can we turn things around before it’s too late? We must start with the girls.

Teenage girls must be listened to and taken seriously. It’s time for the international development community to identify them as a priority target, one that must be consulted when implementing and evaluating new programs and services. The top-down approach has failed too often.

Girls must be the focus of targeted funding. But for that to happen, they must be properly identified first. Data must be compiled and analyzed in a much smarter way, classifying people not only by sex, but also by very specific age segments (10-14, 15-19). Failure to do so will result in ineffective programs, and further waste of aid money.

Sexual violence against girls must be increasingly addressed at both international and national levels. There is a chronic data deficit worldwide, as victims often don’t report rape. Even in countries such as the UK, only 15% of all victims of rape come forward. Much more has to be done to reassure young girls that justice is firmly on their side, preventing them from falling into the trap of self-blame.

Countries that don’t meet their obligations in enforcing the rule of law must be held accountable. Perception polls are a good to way to start, especially when data is lacking. The latest expert poll on women’s rights by the Thomson Reuters Foundation showed India to be the most dangerous country for women within the G20. The finding came six months before the infamous Delhi gang rape, and has since been used extensively by activists to demand change.

Education, however, must top all priorities. Placing girls in a safe learning environment means reducing their chances of being sexually or economic exploited, or married off as child brides. Giving girls the right skills means making sure they enter adulthood as active citizens, with more choice in life. It’s a matter of human rights, but also an investment that could solve global challenges. On average, 70% of every woman’s salary is spent directly on her family. This has obvious positive consequences for society at large.

It is estimated that just one additional year of secondary schooling can boost girls’ future earnings by 15-25%. In practical terms, that means that if girls in Nigeria had the same employment rate as boys, the country would add $13.9billion annually to the economy. In Kenya, this would add $27billion to the national GDP. In India, four million adolescent illiterate mothers translate into a loss of over $383billion in potential lifetime income.

There are tipping points in history that must be exploited. And the tipping point for gender seems closer than ever. But to trigger real change, we must be strategic and tackle the root of the problem, not just the symptoms. The main obstacle to girls’ empowerment – from access to healthcare, to safety and education – lies in the many discriminatory social norms embedded within their respective communities.

We know that cultural change is the hardest to harness, but with the active involvement of committed governments at a national level, and with the active participation of men, it can happen. The recent progress in the fight against female genital mutilation in Kenya is evidence that the backing of national governments is essential and can create wide-scale victories. When men see women leaders within their communities they understand the importance of education for their daughters.

Our tipping point is now. It’s time to take action. It’s time to make a radical shift, to start seeing girls not as vulnerable or as a liability, but as potential leaders. It’s time to see girls for who they are: the driving force of their generation, one poised to bring real social change.

Women’s access to healthcare is one of the themes at the forthcoming Trust Women Conference – London 3-4 December. The event is organised by the Thomson Reuters Foundation in partnership with the International Herald Tribune

www.facebook.com/everymothercounts

11 October 2013

By Christy Turlington Burns and Monique Villa

http://www.huffingtonpost.co.uk/christy-turlington/christy-turlington-international-day-of-the-girl_b_4078816.html

Women’s health communities critical to reducing maternal and child mortality in Africa.

Obstetricians and gynecologists, ministers, public health specialists and civil society organizations convened in Addis Ababa, Ethiopia from 2-5 October at the First International Federation of Gynecology and Obstetrics (FIGO) Africa Regional Conference to discuss ways of improving maternal and child health in Africa.

Speaking at the opening, UNAIDS Deputy Executive Director, Programme, Luiz Loures highlighted the link between HIV and maternal and child health. He called for women’s health and HIV communities to closely work together to increase access to life-saving health services to reach the most marginalized in society.  He also stressed the need to uphold the sexual and reproductive rights of women living with HIV.

In sub-Saharan Africa, women are more likely to be living with HIV than men, accounting for 58% of the 22.1 million adults who were living with HIV in the region in 2012. Young women are particularly at risk of HIV infection–– around 28% of all new adult HIV infections in sub-Saharan Africa are among young women between the ages of 15-24. HIV is also a leading cause of death among women of reproductive age and has a major impact on child health and mortality, mainly through the transmission of HIV from mother to child.

Dr Loures congratulated FIGO on its visionary and bold work on women’s sexual and reproductive rights. He also underscored UNAIDS commitment to strengthening its collaboration with FIGO to raise political visibility and engage women’s networks on HIV and sexual and reproductive rights issues to reduce AIDS related maternal and child mortality.

Quotable

Human rights must be at the centre of our practice as everyone has a right to live. Our primary commitment as physicians is to save lives.

Luiz Loures, UNAIDS Deputy Executive Director, Programme

FIGO looks forward to active collaboration with UNAIDS to ensure the protection of the rights of women living with HIV regarding access to their services in the health sector.

Professor Professor Sir Sabaratnam Arulkumaran, FIGO President

Ethiopia has made excellent progress towards achieving the millennium development goals on maternal and child health and we are grateful for the assistance from our partners, such as FIGO and UNAIDS.

Dr Amir Amare, State Minister at the Federal Ministry of Health – Ethiopia

CCMs Will Be Required to Meet New Minimum Standards Starting in 2015.

Wording of one of the existing six minimum requirements has been altered
CCMs will be required to undertake annual self-assessments

The Global Fund has adopted new minimum standards for country coordinating mechanisms (CCMs). The Fund has also modified the wording of one of the six CCM minimum requirements, and has designed a CCM Performance Assessment Tool which CCMs will be required to use annually.

Currently, CCMs must meet the six minimum requirements to be eligible to receive funding for programmes to fight HIV, TB and malaria and to strengthen health systems. As of 1 January 2015, CCMs will also be required to meet the new minimum standards to receive such funding.

Each minimum standard is attached to one of the existing minimum requirements. Thus, in future, for those minimum requirements that have minimum standards attached, determining compliance with both the minimum requirements and the minimum standards will be done at the same time.

Starting in 2014, CCMs will be required to conduct a self-assessment annually using the CCM Eligibility and Performance Assessment Tool. (CCMs can start this process now if they choose to.) The purpose of the self-assessments is to allow the CCM to determine not only if it is compliant with the minimum requirements and minimum standards, but also how well the CCM is functioning. The Global Fund Secretariat says that the self-assessment exercise will produce a “complete diagnostic” of the CCM.

The Global Fund Secretariat is planning to revise the existing CCM Guidelines to reflect the new minimum standards and related changes. Revisions to the CCM Guidelines will likely have to be approved by the Board.

Change to one minimum requirement

The wording of Requirement 4 has been modified to include key affected populations and to add a reference to human rights and gender.

The old wording of Requirement 4 was as follows:

“The Global Fund requires all CCMs to show evidence of membership of people living with HIV and of people affected by TB or malaria (where funding is requested or has previously been approved for the respective disease). People affected by TB or malaria include people who have lived with these diseases in the past or who come from communities where the diseases are endemic.”

For the new wording of Requirement 4, see the table in the next section.

New minimum standards

One of the most significant new minimum standards is the requirement that the number of voting CCM members with a conflict of interest (COI) not exceed one per constituency. (This is related to Minimum Requirement 6 which is about COI.) The minimum standards do not define “constituency.” The Global Fund Secretariat told GFO that NGOs and faith-based organisations are two examples of constituencies in the civil society sector.

Another important minimum standard is the requirement that 40% of the CCM membership be drawn from the national civil society sector. The existing CCM Guidelines recommend that at least 40% of CCM membership be from non-government constituencies.

The new minimum standards also require that the CCM have balanced representation from men and women.

The complete list of new minimum standards is shown in the table below, along with the minimum requirements to which they relate. There are no minimum standards for Requirements 1 and 2.

Table: CCM Minimum requirements and minimum standards adopted by the Global Fund

Minimum requirement and related minimum standards
Minimum requirement #1:
The Global Fund requires all CCMs to: (i) Coordinate the development of all funding applications through transparent and documented processes that engage a broad range of stakeholders – including CCM members and non-members – in the solicitation and the review of activities to be included in the application. (ii) Clearly document efforts to engage key population groups in the development of funding applications, including most-at-risk populations.
Related minimum standards: None.
Minimum requirement #2:
The Global Fund therefore requires all CCMs to: (i) Nominate one or more PR(s) at the time of submission of their application for funding. (ii) Document a transparent process for the nomination of all new and continuing PRs based on clearly defined and objective criteria. (iii) Document the management of any potential conflicts of interest that may affect the PR nomination process.
Related minimum standards: None.
Minimum requirement #3:
Recognizing the importance of oversight, the Global Fund requires all CCMs to submit and follow an oversight plan for all financing approved by the Global Fund. The plan must detail oversight activities, and must describe how the CCM will engage program stakeholders in oversight, including CCM members and non-members, and in particular non-government constituencies and people living with and/or affected by the diseases.
Related minimum standards:
  • The oversight body conducts oversight activities to discuss challenges with each PR and identifies problems, potential reprogramming and corresponding reallocation of funds between program activities, if necessary.
  • The CCM takes decisions and corrective action whenever problems and challenges are identified.
  • The CCM shares oversight results with the Global Fund Secretariat and in-country stakeholders quarterly through he process defined in its Oversight Plan.
Minimum requirement #4:
“The Global Fund requires all CCMs to show evidence of membership of people that are both living with and representing people living with HIV, and of people affected* by and representing people affected by Tuberculosis ** and Malaria*** as well as people from and representing Key Affected Populations****, based on epidemiological as well as human rights and gender considerations.
* Either people who have lived with these diseases in the past or who come from communities where the diseases are endemic
** In countries where Tuberculosis is a public health problem or funding is requested or has previously been approved for Tuberculosis
*** In countries where there is on-going evidence of Malaria transmission or funding is requested or has previously been approved for Malaria
**** The Secretariat may waive the requirement of representation of Key Affected Populations as it deems appropriate to protect individuals”
Related minimum standard:
  • The CCM has balanced representation of men and women (the Global Fund Gender Equality Strategy clarifies how women and girls are key affected groups in the context of the 3 diseases).
Minimum requirement #5:
The Global Fund requires all CCM members representing non-government constituencies to be selected by their own constituencies based on a documented, transparent process, developed within each constituency. This requirement applies to all non-government members including those members under Requirement 4, but not to multilateral and bilateral partners.
Related minimum standards:
  • CCM membership comprises a minimum of 40% representation from national civil society sectors.
  • CCM has clearly defined processes of soliciting inputs from and providing feedback to their constituencies that selected them to represent their interests in the CCM.
  • The CCM elects its Chair and Vice-Chair(s) from different sectors (government, national civil society and development partners ) and also follows good governance principles of periodic change and rotation of leadership according to CCM by-laws.
Minimum requirement #6:
To ensure adequate management of conflict of interest, the Global Fund requires all CCMs to: (i) Develop and publish a policy to manage conflict of interest that applies to all CCM members, across all CCM functions. The policy must state that CCM members will periodically declare conflicts of interest affecting themselves or other CCM members. The policy must state and CCMs must document that members will not take part in decisions where there is an obvious conflict of interest, including decisions related to oversight, and selection or financing PRs or SRs. (ii) Apply their conflict of interest policy throughout the life of Global Fund grants, and present documented evidence of its application to the Global Fund on request.
Related minimum standard:
  • To guarantee effective decision making, the CCM ensures that the number of members in the CCM with CoI does not exceed 1 person per constituency (excluding Ex-Officio Members with no voting rights).

CCM Performance Assessment Tool

The Global Fund Secretariat says that the self-assessment of the CCM using the new CCM Performance Assessment Tool will produce a complete diagnostic that takes into account information from in-country partners. The tool is available (in English) on the Fund’s website here. The Global Fund says that other-language versions of the tool will be posted soon.

The Secretariat requires that CCMs request technical assistance (TA) when they conduct the self-assessments. A partial list of TA providers is available on the Global Fund website here. Additional providers will be added to the list in future. CCMs wishing to use a TA provider not on the list must consult their fund portfolio manager. The plan is that all TA providers working on the self-assessments will have received training on how to conduct them. The Secretariat told GFO that the goal is to ensure a consistent approach to the self-assessments across all CCMs.

According to the Global Fund, the TA provider will work with the CCM to analyse the internal functioning and dynamics of the CCM and conduct interviews with key in-country stakeholders. In the process, the TA provider will produce an improvement plan for each CCM, which will be submitted to the Global Fund Secretariat. The Secretariat will review each self-assessment.

CCMs that are fully compliant will be granted “CCM Eligibility Clearance” for one year from the assessment. This clearance allows the CCM to submit a concept note without having to go through a CCM eligibility screening process for Requirements 3–6. (However, Requirements 1 and 2 will be assessed at the time of concept note submission.

Note: In 2014, CCMs need to be compliant with the six minimum requirements (as is the case now). Starting on 1 January 2015, CCMs will also need to be compliant with the new minimum standards.

The Global Fund says that for CCMs that are non-compliant, TA providers will support the CCM to elaborate a milestone-driven improvement plan. The Global Fund Secretariat must approve the plan. According to the Fund, “non-adherence to the improvement plan will impact current and future funding.”

The CCM Performance Assessment Tool was used by the CCMs participating as early applicants in the transition phase of the new funding model.

Information for this article was taken from the CCM pages of the Global Fund website and from direct communication with the CCM Hub at the Secretariat. GFO plans to write a more detailed article on the CCM Performance Assessment Tool in the near future.

By David Garmaise

5 October 2013

http://www.aidspan.org/node/1923#comment_section

Secure Africa’s Future by Ensuring Sexual and Reproductive Rights and Health for All.

African government leaders meet this week in Addis Ababa, Ethiopia, to chart a forward-looking agenda building on commitments made at the landmark International Conference on Population and Development (ICPD) in Cairo in 1994. At that conference, governments placed the human rights and empowerment of women, including their reproductive health and rights, squarely at the center of population policies and sustainable development.

As former president of Mozambique, I join with others in pride for the progress we have achieved. Policies and programs inspired by Cairo have saved and improved millions of lives in Africa. They have been levers for our continent’s increasing dynamism. But more needs to be done to ensure a prosperous tomorrow, one where all our people enjoy their rights, dignity and health. The future of Africa is at stake.

As co-chair of the High-Level Task Force for ICPD, I know that if governments agree to uphold sexual and reproductive rights and health for all, they will also be helping Africa reduce poverty and meet its development objectives, while capitalizing on current economic growth.

In spite of recent progress, grim realities cannot be ignored. Sub-Saharan Africa accounts for over half of the 800 maternal deaths that occur globally each day. Our region’s rate of unsafe abortion is the highest in the world — over 5 million each year — with 25 percent performed on adolescent girls. More than 45 percent of African women and girls experience physical and/or sexual violence in their lifetime. Thirteen million African girls under 18 are married, increasing their risks of early child-bearing, HIV, persistent poverty, and domestic violence. And over 4 million youth in Africa are infected with HIV.

These are preventable problems with cost-effective solutions. Solving them is a matter of political leadership, backed by resources. No country can afford to forgo opportunities to make sexual and reproductive health and rights a reality in the 21st century. These priorities are keys to unleashing the full energies and talents of our people, especially women and young people. They must be pillars of any sound post-2015 global development agenda.

The High-Level Task Force for ICPD calls upon leaders to consider four policy recommendations crucial for Africa’s development transformation:

  1. Enact legal and policy reforms that respect, protect and fulfill sexual and reproductive rights for all. We must repeal legal barriers — including restrictions on access to contraception and safe abortion — that block women and young people from getting the sexual and reproductive services they need. We must reject harmful social norms of control over human sexuality, including those related to sexual orientation and gender identity. Too many of our brothers and sisters face horrific acts of violence and discrimination on this basis. This is not the Africa we want.
  2.  

  3. Accelerate universal access to quality sexual and reproductive health information, education and services. No woman or adolescent girl should die giving birth, or from complications of unsafe abortion, a major killer of our women and girls. This is a grave social injustice: Where abortion is illegal, it is the poorest women and girls who risk their lives.
  4.  


  5. Guarantee universal access to comprehensive sexuality education for all young people, both in and out of school. Youth-friendly sexual and reproductive health services and comprehensive sexuality education are keys to empowering Africa’s 300 million young people, preventing early pregnancy, halting the spread of HIV and promoting gender equality. They are also essential, alongside quality education and decent work opportunities, to realizing the full potential of Africa’s demographic window of opportunity.
  6.  


  7. End violence against women and girls and impunity for perpetrators. We must focus on prevention, putting a stop to violence against women and girls in the first place. To do this we must engage men and boys from all walks of life. And we must end child marriage and female genital mutilation within a generation. It is also high time that we secure universal access to critical services and access to justice for all victims and survivors of gender-based violence.


Leaders gathered in Addis have the opportunity to adopt an agreement to fully meet the needs and rights for all, with the empowerment of women and young people and sexual and reproductive health and rights at the center. This will put us on the right path to bolster the resilience of our people and families, the vibrancy of our communities and the sustainable, inclusive growth of our nations.

Joaquim Chissano is former president of Mozambique and co-chair of the High Level Task Force for ICPD, a group of government, civil society, and private sector leaders working to ensure that sexual and reproductive health and rights is central to the global development agenda.


by Joaquim Chissano

Former president of Mozambique; co-chair, High-Level Task Force, ICPD

http://www.huffingtonpost.com/joaquim-chissano/africa-sexual-reproductive-rights-health_b_4005108.html